Endometrial Receptivity and the ERA biopsy

Endometrial Receptivity and the ERA biopsy

Everyone would agree that functionality of the uterine lining is incredibly important for implantation of the blastocyst to take place. The question of how to measure this, termed ‘uterine receptivity’, has been studied extensively in the literature. The methods that have been used in the past were indirect, assumptive and not reproducible. Researchers in Spain have created a new tool which has been shown to be promising for identifying molecular markers for uterine receptivity.

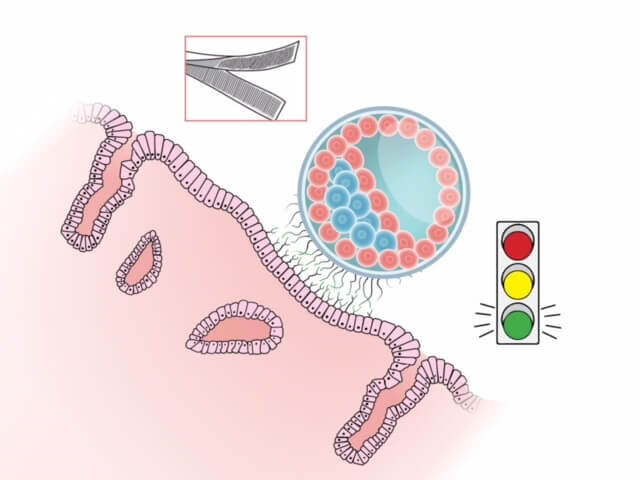
Remarkably, as the blastocyst floats within the uterine cavity looking for a place to land, a dialog takes place between the blastocyst and the endometrium. In order for a successful implantation to take place, the blastocyst needs to be at the appropriate stage, and it needs to signal the uterine lining to ‘accept’ it. Within the uterine cavity, once ready for implantation, the microvilli present on the trophoblast cells of the blastocyst act as one side of ‘velcro’ to adhere it to the uterine lining. The embryo is in search of a receptive endometrium (the other half of the velcro) which will ‘fasten it’ to the uterine wall. The hormonal preparation of the uterus plays a critical role each month in creating this environment in which the blastocyst can adhere to the endometrium in the hope that implantation will take place.

The uterine lining undergoes changes during the two phases of the menstrual cycle that prepare it for blastocyst implantation. During the proliferative phase, it grows due to the increasing production of estrogen by the ovaries. The second phase is called the secretory phase where the production of progesterone, produced by the corpus luteum, converts the endometrial lining to a secretory one, changing the cells to prepare for implantation (a process called decidualization). Should implantation not take place, the hormone levels will fall, resulting in a shedding of the lining, which results in menses. Studying the mid-secretory phase is of great importance since the window of implantation (WOI) takes place then. The sweet spot of WOI is approximately a 2-day period when the uterus is prepared to accept the implantation of a blastocyst. Conventionally, it was assumed that every woman had the same WIO, (approximately 8-10 days after ovulation) so embryo transfers would be scheduled to take place during this time. This theory has recently been challenged, with researchers proposing that the WOI can vary among women.

Research has been done extensively to detect and determine criteria necessary in order to call an endometrium ‘receptive’. In the past, this was done using histological criteria, i.e. the microscope appearance of the endometrium (termed the Noyes Criteria). Certain days of the menstrual cycle have typical microscopic characteristics and a pathologist would determine if the sample looked like day 16 or 17..etc (dates were reported with ovulation normalized to day 14-so an endometrium that was day 17 by Noyes Criteria should be 2 days post ovulation). As one can imagine, there is much variability and subjectivity in this interpretation between pathologists, plus womens’ cycles can show considerable variability. Also, just because the cells have the appearance of a typical cycle day 16, for example, doesn’t mean that the lining is actually receptive. That would just be implied. As a result of these limitations, and some recent studies that found this morphological dating method to have poor predictive value, this method of assessing uterine receptivity is no longer widely used.

One can also look at the appearance of the lining by ultrasound in the late proliferative phase. Many studies have focused on the endometrial thickness and type (triple-line vs homogenous appearance). Although the lower limit of an acceptable lining has not been agreed-upon by researchers or practitioners (most would arguably be satisfied with a lining of 7 mm or above) that information is a reflection of the adequacy of the proliferative phase, which tells us that the lining was properly primed by estrogen, but doesn’t give us any information other than that. Ultrasound in the secretary phase is not helpful, as it shows a thick, homogenous lining that doesn’t usually affect clinical decision-making, so is not routinely performed.

Over the last decade, different ways of studying the endometrial lining more directly have been investigated, first by attempting to identify the substances that were generated at the time of implantation, the cytokines, adhesion molecules and other proteins. To date, this line of investigation has been unsuccessful, so the focus has shifted to the stage that leads to the production of these substances, the stage of RNA transcription. Transcriptomics allows the study of gene expression by looking at the mRNA produced. It can provide a molecular profile of the status of the endometrium by telling us what genes are actually “turned on”. Gene expression profiling is now widely used for other disciplines, such as tumor classification.

With the relatively recent advent of DNA microarray analysis we can measure the expression of thousands of genes simultaneously, allowing us to explore which ones are expressed in the mid-secretory phase, when implantation takes place. The discovery of this technology was a major turning-point in the study of endometrial receptivity and several studies were undertaken to determine which of these genes were important during the WOI. Researchers agree that there is a specific and unique action that takes place during the process of transcription, when RNA creates the ‘script’ for a protein, in order for the endometrium to become receptive, but the identification of the specific genes involved was elusive until recently. A group in Spain identified 238 genes related to endometrial receptivity and collected the data to create a tool, named the endometrial receptivity array or ERA (Diaz-Gimeno, et al 2011). This test purports to identify if an endometrium is receptive or not based on the mRNA profile or the endometrial gene expression. It further differentiates the non-receptive category into pre- or post-receptive) in natural or hormone-replacement (HRT) cycles, regardless of it’s appearance by ultrasound or under the microscope (histological). This group then applied their tool by testing it on patients with recurrent implantation failure (RIF) by performing a multi-center, prospective study. What they found is that the WOI was ‘displaced’ in 26% of the women with RIF, so in 1 out of 4 patients with RIF, dysynchrony between the blastocyst and the endometrium might be to blame (Ruiz-Alonso, et al, 2013). They then did a second ERA test on the patients who had the displaced WOI to confirm that by adjusting the progesterone start or transfer day (see more on this below) increased implantation rates. They performed a subsequent adjusted embryo transfer (termed a personal embryo transfer or pET) and demonstrated a 50% pregnancy rate and a 38% implantation rate in this group of patients (which is the rate similar to the control group who did not fail a treatment cycle). This data supports the concept that the conventional window of implantation differs among women (at least a fourth of us) maybe only slightly in some cases, but enough to preclude implantation.

The test is performed in the secretory phase of either a natural cycle or a hormone replacement (HRT) cycle. If during a natural cycle, then the biopsy is done on LH surge + 7 . If during an HRT cycle, then the biopsy is performed on exogenous progesterone start + 5 (120 hours post start of progesterone). The biopsy sample is sent to the lab and analyzed (this takes approximately 2 weeks) and results are termed either ‘receptive’ or ‘non-receptive’. If non-receptive, it further analyzes the sample as pre-receptive or post-receptive. If pre-receptive, then the patient needs more time (hours or days) of progesterone, so the progesterone is started earlier or the transfer is moved later. If post-receptive, then the WOI has already passed, so the recommendation would be to start the progesterone later or move the transfer earlier. The recommendation is to repeat the cycle after modifying it according to the suggested intervention (more or less days of P) and the biopsy is redone to confirm that the endometrial tissues sent now receptive. This step is center-specific with some practices often performing a repeat mock cycle with biopsy and others only occasionally repeating it, but still using the recommended progesterone modifications for the frozen embryo transfer cycle, thereby creating the patient’s personalized embryo transfer(called pET). For more information on the specifics of the results and testing criteria, see the video here.

Although the data collected so far is promising, there are some limitations in the study design that should be considered when interpreting results. One is that all of the studies performed so far have relatively small sample sizes. Another is that there was no effort (in most studies) to separate out the embryo quality so that this important variable could be controlled. (There is a recent, retrospective study, in Japan where the researchers only transferred back euploid embryos with optimistic results, but it was retrospective and had a small sample size.) Furthermore, in the initial ERA studies, the non-receptive group was not further stratified to include a segment who did not have pET prior to their next transfer, so it is not known if they would have been pregnant just due to trying again, without further intervention. Finally, keep in mind that if 25% of RIF patients had a displaced WOI, 75% did not, implying that there are other factors (embryo quality among them) that could be the cause of implantation failure.

The importance of determining the timing of endometrial receptivity has always been emphasized in reproductive endocrinology. Now, instead of just relying on the way the endometrium appears, either by ultrasound or microscopically, some researchers suggest that we have the added benefit of being able to study the molecular changes that happen within the endometrium and act on these results to form a personalized prescription for subsequent transfers. Although exciting, further studies are needed to confirm this small subset of studies and also to determine if this test will be useful for an expanded group of women (Currently it has been suggested that it should be offered to those who have failed >2 IVF cycles or >1 donor oocytes cycle.) Methods of non-invasive testing are also being explored and might be a viable option within the next decade. The idea that every woman has their own personalized window of implantation (and that we can determine and take advantage of this) is a new and exciting concept in REI.

Special thanks to Paul Bergh, MD, FACOG For his assistance with editing this article.

slot gacor

toto

toto togel

link gacor

slot gacor

slot gacor

kampungbet

slot gacor

situs gacor

situs togel

slot gacor

situs toto

link slot

toto

situs gacor/a>

kampungbet

kampungbet

kampungbet

kampungbet

situs gacor

To My Friend’s Daughter

This photo was taken during the first hour of a seven-hour car ride that was as crazy and stressful as you can imagine it would be. My kids couldn’t seem to coordinate their bathroom breaks, there was bad traffic, and many, many squabbles in the car where I threatened some unmentionable actions and said things that I regret.


The calm before the sh*t storm


But you would never know just by looking at this picture. What would have been real and accurate is if I took a before and after photo, the ‘after’ taking place in the throes of crazy, when I was sweating and talking to myself. In fact, if I’m being honest, even though they start off well-intentioned, most of my long car trips end like this one, where we are all fighting and fussing. But we don’t show that stuff, those unvarnished emotions, to the world because they are deemed unacceptable. Instead, we process them, suppress them or package them up in a nice little box or, in this case, an acceptable picture. There’s a stigma, still, attached to being authentic and admitting that you are struggling.


In my role as an infertility nurse and nurse educator, I often function as a patient concierge, counseling people during their fertility journey. Some formally, but many people informally. I can’t tell you how many times I am approached by a friend who has read one of my blogs and asks me to talk to their daughter, family member or friend about what they should do when they are ready to conceive. I do talk to them, and I actually cherish these interactions, being able to demystify or explain complex processes.


Lately, I’ve been speaking to those who are not actively trying yet, and we discuss what they can do prior to pregnancy. I go over the basics, taking vitamins, getting immunized, achieving a healthy weight, but what I really want them to know is that preparing for pregnancy (whatever that path looks like for them) is an inside job.


Here is the irony about female fertility: You don’t know if you can conceive unless you try and you can’t try until you are ready to have a baby. There are no previews or glimpses into the important machinery that is the female reproductive system, so we can’t ‘prep’ for it until we are ready to ‘use’ it. This is a foreign and uncomfortable concept to most of us.


Think about our past experiences which form the context for this current one: we have an important test, we study for it. We are running a race, we train for it. You decide to start a family and you, well, go for it. Fertility (within reason and depending on age) follows a bell curve, like many processes in life, so that the majority of people get pregnant in a few months. Some get pregnant right away, and we know this because we are often inundated with these stories, like folklore. Most take a few months, and some need assistance from a fertility clinic to conceive. I can tell you, though, that I review lots of pregnancy records for my clients and a women might ‘remember’ that she got pregnant in a month, but the OB/GYN records state 3-4 months. It’s just all about perception.


Many of my friend’s daughters are reluctant to call me, either because they are embarrassed, or just don’t want to label that they are trying-because then, if it doesn’t work, they have failed at something. Many of them are ‘not not trying’, which I assume means not using birth control and having sex for fun instead of on certain days of the month.


Why do we, as women, feel ashamed or embarrassed to talk about this kind of stuff? Social media doesn’t help as it perpetuates a myth that everyone is happy, that situations are under our control most of the time and, when they aren’t, they are handled with humor and grace. If we are being authentic, we know this isn’t true and I am guilty of perpetuating this as well.  I post pictures of my kids and my life (like the one above) that don’t truly reflect the fissures in it, posed pictures while everyone is smiling or funny ones where it seems like I’m laughing at something when I wanted to yell or cry. I still felt the frustration that the situation generated, but took the picture once it was over and processed. So, it probably never really got resolved, just repressed and reframed.


Why do we correlate importance with what’s visible?


This is what happens to young women who are struggling with infertility. They feel the anxiety of trying or wondering when to try, how to try, but then internally compartmentalize it so that they can seem ‘normal’ to their OB/GYN or family members. This is the snapshot that we see on social media, not the real person with real feelings. I talk about this with my patients.


One in particular is so incredibly put-together while she is on the phone, regardless of whether it’s good or bad news. But once, in an unguarded moment, she revealed to me that she is a ‘mess’ after she hangs up the phone. She’s not a mess. She’s a deeply feeling person in a messy situation. There is a difference. But I can reassure her many times and the message might be received but not heard, or heard but not absorbed.


I am working on a venture to develop strategies for nurses to help them find joy in their jobs. I am helping to write protocols, educate them and refine their systems so that they are more efficient. What I can’t emphasize enough, though, is that the women need to do the inner work.


External factors and stressors will always be present. We need to feel that we are good enough, strong enough, just ‘enough’ regardless of our path or outcome. I’m not an expert in this field, and am just beginning to study it. But I  have spoken to a few who are well-versed in it, and here are some of the activities that they recommend for developing inner strength:


  • Journaling or writing. I started writing my blog posts as a form of stress release after a difficult patient conversation and find that they are just as helpful to me as they are to others. It was difficult for me to reveal how I felt on that car trip, and allow myself to be vulnerable, but vulnerability is a powerful tool, for more on this, read this excellent book by Brene Brown.


  • Going outside for a walk or exercise. It’s not just about the aerobic activity, it’s about the contact with nature and invoking your senses to try to get you to focus on the present moment. If the weather precludes outside activity, go to the gym to move, but smelling the leaves or feeling the sun on your face or putting your feet in the sand brings you back to the present. Nature can stop, if even only for a few moments, your mind from going down the well-worn path of would-haves and should- haves and endless ruminating and thought-looping in which we have a tendency to engage.


  • Meditation. This one is tough for me, but I highly recommend the work by Dan Harris on this subject. He became interested in happiness and meditation after having an on-air panic attack that millions witnessed. As a result, he became interested in the healing powers of meditation, writing a book and developing an app, both of which I’ve found incredibly helpful. It’s easy reading and he somehow manages to be both informed and self-deprecating.


  • Reading. I love to read, but need to be picky about the tone and subject matter of the book depending on my mood. Sometimes I want to learn, sometimes I want to laugh, sometimes I want to escape. If you need ideas for good books, check Pinterest or go to the GoodReads app to see what your friends recommend.


  • Talk to a friend. Most likely your friends have struggled with some issue in their life, maybe not infertility, but something that they needed to manage. It’s ok to share your challenges with them. Most are grateful that you are willing to open up to them. Your job, in return, is to cultivate your listening skills. This book by Celeste Headlee really helped me with this and I recommend it to all of my clients and friends.


I am happy to talk to you or your daughters about their fertility. Honored, actually. But some of you ask me what you can do, besides refer them to me. In this situation, you don’t have to be an infertility nurse to make a difference.  Encourage them to develop inner strength. If you think they are struggling, ask them, as their Facebook posts aren’t always a reliable reflection of their inner psyche. Support them in the knowledge that it’s ok to allow external events to affect you, without defining you.


“A healer is not someone that you go to for healing. A healer is someone that triggers within you, your own ability to heal yourself.” –Unknown

slot gacor

toto

toto togel

link gacor

slot gacor

slot gacor

kampungbet

slot gacor

situs gacor

situs togel

slot gacor

situs toto

link slot

toto

situs gacor/a>

kampungbet

kampungbet

Discomfort

I often role-play with nurse clients as I find it is an important teaching tool in exposing the nuances of patient care gaps that aren’t obvious by using traditional methods.


For example, I use this format when reviewing how to convey negative results, where I become the ‘patient’ on the receiving end of the phone call. Last week, during a client coaching session, my ‘nurse’ told me about my negative result, then quickly advised me about calling with my next Day 1 to start the process again.


When we later analyzed the conversation, I pointed out the haste in which she discussed next steps, arguably before I had a chance to process the bad news – a common complaint that I’ve heard from patients over the years. My ‘nurse’ admitted that she knew she was rushing, but was afraid that I would ask her something that she didn’t know, or would express an emotion that she couldn’t handle, one that would make her uncomfortable. But discomfort can be a potent tool, enhancing the patient experience, particularly during an emotionally-charged interaction.


Learning to embrace discomfort was a lesson that I learned 20 years ago in a yoga class, when my teacher told us that once we get deeply in the pose, that we are actually just getting started. The ‘work’ of the pose is what you do from there, when your legs are shaking and you are sweating and hoping that she remembers to count the seconds, and not forget while talking to another student.


You have a choice: do you stay, let up, or go deeper, curious to explore what happens after that? Never to the point of pain, but not skirting around the feeling of deep sensation, sensation that is uncomfortable. The times that I persevered, I discovered something new. Maybe that my legs were weaker than I thought, maybe that my right side was stronger than my left, and, after years of practice, maybe that I had feelings that were stuck, that needed permission to be released. I even found myself tearing up without any warning in class. This is not uncommon, according to my teacher, particularly during hip and shoulder opening poses since many of us hold onto stress in those spots.


This taught me something else about discomfort. It is the result of many factors, not the least of which is that it can be a sign you have triggered something unresolved in your own life. Had I not pushed, not crossed that threshold from content to discontent, I would have missed out on growth potential. I discovered an insight that, in retrospect, has proven to be important in my personal and professional life.


Ok, back to how this applies to being an infertility nurse.


I’ve learned to feel honored to be the go-to nurse in the offices I’ve worked in for relaying negative pregnancy test results to patients. Of course, I don’t enjoy the part of my job where I have to sever the hope of a patient that she achieved a pregnancy that month. I do, however, realize the weight of my contribution to this challenging conversation. Even though I can’t change the news, I can positively affect the experience of receiving it.  I find that applying this perspective gives my role the appropriate level of reverence and gravity that it deserves.


I invite you, as the nurse, to experience what it feels like to settle into the pause between giving bad news and advising of next steps. Allow the patient to express whatever she is feeling and just listen, as awkward or uncomfortable as this may make you. No empty words or platitudes, no story about your own life or other patients’ journeys unless she asks.


By pausing, you are creating an environment that gives her permission and space to mourn a loss. If she asks, “why,” you can answer honestly, and appropriately, that you don’t know. That she may never have an answer to this, but that she can rely on you, and you will be there to guide her through the next steps. If she asks what these are, then advise her to call with Day 1. If she’s not there yet, then maybe the ‘next step’ conversation takes place the next day on a subsequent phone call.


[amazon_link asins=’1592408419′ template=’ProductAd’ store=’fertileheal04-20′ marketplace=’US’ link_id=’019a1f78-2a2e-11e8-ab17-81713c8cc1db’]Realize that, at this time, the person who needs to feel heard is the patient, not you. At worst, she will be upset or angry and you won’t know how to respond, and maybe all you can do is express regret or apologize. Allowing yourself to be vulnerable also has its benefits by promoting human connection, just ask [amazon_textlink asin=’1592408419′ text=’Brene Brown’ template=’ProductLink’ store=’fertileheal04-20′ marketplace=’US’ link_id=’9075476b-2a2d-11e8-8580-6fccfb0ae5bf’].


As a disclaimer, I am just asking you to listen, not advocating that you absorb the patient’s pain. This can lead to compassion fatigue, a very real and damaging potential consequence of being a health-care provider.


Finally, whenever you have to impart bad news to a patient, you may be tempted to hasten the delivery of the news or end the phone call quickly. Consider this first: settling for being comfortable can lead to complacency and missed opportunities for both you and your patient.

Subscribe

Subscribe to our monthly Newsletter for more valuable content.


situs gacor

togel

togel

situs gacor

situs gacor

situs gacor

kampungbet

situs gacor

slot gacor

situs toto

slot gacor hari ini

toto

situs slot

situs toto

link gacor/a>

kampungbet

kampungbet

Overeating: It’s not just about self-control

You might notice that some people seem to be able to maintain a healthy weight effortlessly while others really struggle. Maybe you personally fall into one of these two groups and it’s difficult for you to relate to the other.


However, gaining an understanding of the reasons why people struggle to lose weight can help give you a better perspective when working with overweight or obese patients.


Traditionally, we are told that gaining or losing weight adheres to a mathematical formula: if caloric intake = caloric expenditure, you maintain weight. Following that same logic, caloric intake > expenditure = weight gain, and caloric intake < expenditure = weight loss.


But we are human beings, not math problems, so we have some nuances that are not addressed by a simple formula.

Satiety is the result of a cascade of events. It starts with the sensory perception of food, called the cephalic phase. Cephalic phase responses (CPRs) are physiologic responses that your body has when presented with the sensory aspects of food (such as sight, smell and taste) which communicate with the brain and advise it to start the process of digestion (Smeetz et al, 2010).


Your body starts the process of achieving fullness even before eating a bite of food. As you eat, there are receptors in the stomach that respond to the volume of food once it arrives there. As the stomach expands, due to the bulk of food or liquids ingested, signals are sent out to eventually stop eating.


Hormones also influence eating patterns. A substance called leptin, known as the ‘satiety hormone,’ is produced by fat cells after someone eats. Leptin is part of a feedback system with the hypothalamus, a structure in the brain that controls, among other things, appetite.


When the system is working properly, increased leptin levels signal the brain to stop eating. Another hormone, dopamine (sometimes known as the feel-good hormone because it is secreted in response to activities that, well, make you feel good) is released when visualizing food or thinking about eating. This process is termed the ‘dopaminergic reward system’ as it activates reward centers in the brain so that people get a rush, so to speak, from eating. How much of a perceived reward is not the same for everyone, and this difference can also be an important contributor to over-nutrition (Val-Laillet, et al, 2015).


Ok, so with all of these mechanisms in place, how can anyone be overweight? Must be due to lack of self-control, right?

Actually no, and here’s why: Unfavorable genetics are largely to blame. Some people are born with glitches in the satiety system at any and all levels.


For example, human and animal research seems to indicate that certain types of gut bacteria make it harder to lose weight (Million et al, 2013). In one experiment, lean rats who had no endogenous stomach bacteria were injected with the bacteria of either rats who were obese or rats who were lean.


Guess what happened to the lean rats who were injected with the obese rat bacteria? They gained weight. So, it seems that people who have this gut bacteria are already prone to being overweight before they even put food in their mouth. Wouldn’t it be great if we could all be injected with lean-weight gut bacteria? I’m sure this is in our future but, unfortunately, we are not there yet.

Metabolic differences can make some more prone to overeating. Studies that compared dieters (people who diet frequently and, therefore, are likely overweight) with non-dieters found that dieters need to eat less than non-dieters just to maintain weight. Any extra calories, then, are converted and stored as fat in this group.


The cause of this could be that they are dieting and restricting their intake or that being overweight puts them at risk for this, but the outcome is the same: it’s easier for this group to gain weight while eating the same amount as some of their peers. Not fair, right?


Remember the dopaminergic reward system? There is emerging evidence that people who are obese have differences in their genes that affect dopamine signaling, such that their reward centers are hyper-responsive to food cues. They are susceptible to food cravings and overconsumption because they get a bigger ‘rush’ from seeing or eating food more than their lean counterparts do (Val-Laillet, et al, 2015).


This dysfunctional system can be so strong that it overrides the normal controls and feedback systems in the body that are in place to assure caloric and energy equilibrium. The reward centers for lean people may be less responsive to food, so it’s less of an effort for them to push the bread basket away or leave food on their plate. For them, eating isn’t the source of intense pleasure, so they are not as tempted by appetizing food, which may be misconstrued by others as self-control. If the above isn’t bad enough, there is something called, ‘leptin resistance.’ If you recall, leptin is the satiety hormone, the one made by fat cells that signals the brain to tell it to stop eating. Well, it has been found that obese people can have even higher levels of leptin than their lean counterparts (this makes sense since obese individuals have a more adipose or fatty tissue) but not be as sensitive to them (Myers, et al, 2012).


As a result, even with these high levels, obese people still have a desire to eat. This becomes a vicious cycle where the leptin resistance leads to overeating, which increases fatty tissue, which increases leptin (but the brain doesn’t respond to it) and the cycle perpetuates itself. As of now, there is no ‘cure’ for this.  Although some pharmaceutical approaches to increase leptin sensitivity appear promising, none are currently approved.


Don’t rush the soup. All of the above factors seem to make it easier for naturally lean people to succeed, and create very real challenges for people who are obese. These challenges aren’t insurmountable though. There are some strategies that might help. Taking extra time to smell and savor your meal before you eat it prolongs the cephalic phase of satiety and allows extra time for your body to recognize that it might be full. Eating soup or drinking water prior to eating can induce greater fullness by delaying gastric emptying, and stomach distention stimulates the gut receptors to tell the brain to stop eating. Also, there is some data to show that people can reset their leptin levels with long-term healthy lifestyle changes like eating whole foods that take longer to digest and exercising regularly.


Most importantly, for us in the health care industry, it’s important for us to not judge others who are overweight. Weight bias seems to be one of the few remaining acceptable biases left. Studies on weight bias report that overweight people have been labelled as ‘lazy, awkward and non-compliant’ as well as other hurtful and deleterious terms, even by the medical providers who take care of them (Foster, et al, 2003). As you can imagine, then, even a perceived weight bias by you or someone in your practice would negatively affect patient care and retention of overweight or obese individuals.


Related: How to talk to your fertility patients about their weight without seeming like a jerk


Since obesity is on the rise in the U.S., and an increasing number of our patients will be affected by this, it’s incumbent on nurses to understand what leads to over-eating.


We need to realize that eating behavior is multifactorial, the result of a complex interplay of many factors, only some of which are addressed here. Blaming over-nutrition on a lack of self-control is not only unkind, it’s untrue. Please realize that any discussion of weight should be done kindly, compassionately and with the knowledge that, for some, the decks are stacked against them.


References:


Foster, et al. Obesity Res 2003, 11: 1168-77.


Million, M. Et al. Clin Microbiol Infect 2013, 19(4): 305-313.


Myers, M.G. Et al. Cell Metab 2012, 15: 150-156.


Val-Laillet, et al. Neuroimage Clin 2015, 8: 1-31.


Sheets, et al. Nutr Rev 2010, 68(11), 643-55.


Subscribe to Fertile Health Happenings

* indicates required


Tell us a little about yourself


kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor

Letter to my patient

Dear Wonder Woman,

You are beautiful and you are not just a sum of your (sometimes seemingly faulty) parts. Because that doesn’t take into account your spirit and grit as you proceed on this path.

This journey, although tortuous at times, will make you stronger, even if you don’t see it right now. We will go through it together. I can’t possibly imagine how you feel, but I do know that you feel and that you feel deeply.

I care so much about you and your outcome, that I sometimes seem insincere. You might think I am flippant or not listening but I am actually protecting myself. It’s often that the thought of feeling helpless, incompetent, even futile, haunts me long after I hang up the phone or leave the room. Sometimes I lie in bed at night thinking if there is anything else I could have done, anything else I could have said….

If I could give you some advice, it would be that it’s so important to take care of yourself and allow others to take care of you. This is not being selfish, it’s practicing self-care. This is nourishing yourself at a time when you might feel that the outcome is out of your control.

And here is a secret: we experienced infertility nurses aren’t impervious to your discomfort during this process, even though you might not see us angry or sad or frustrated. Every time that we draw blood, we bleed for you. Every time we (inadvertently) hurt your feelings, we hurt too. Every time you feel pain, we ache too.

But every time you are ready to start again, we are right there with you, hopeful, excited and optimistic because we know that, for almost everyone who hopes to conceive, there will be a positive outcome.

So, my final thoughts are an echo of my first.

Please try not to let this process define you. Here is how I would define you: worthwhile, strong and amazing. Even when you don’t feel that way, you are. I should know, I’m the expert.

Finally, I want to thank you for teaching me to be a better nurse and person, just by knowing you and allowing me to care for you during this private and emotional time.

For this, I am grateful.

Subscribe to Fertile Health Happenings

* indicates required


Tell us a little about yourself


kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor

Why Didn’t I think of this before? The Life Lesson that I Learned at a Tennis Clinic

Disruptor – I thought it was just the name of a Pearl Jam song.

It’s a term that I learned about a few weeks ago at a tennis clinic, although I’m sure that most (savvier than me) people have already heard of it.

In tennis, it has to do with your opponent disrupting your rhythm or comfortable playing style. If you like to hit hard, they hit soft, lob or drop shot. I hate those matches, honestly. They are not fun and I often lose to opponents who are, in my opinion, not as good/athletic as me. And then I complain about losing and how “not fun” the match was. I take my long car ride home kicking myself for not respecting their game and forcing my way of hitting on them which, clearly, didn’t work.

The coaches at this clinic (the awesome Billy and Matt Previdi) told us that not only should we respect disruptors, but that we should become one. What? Why would I lower myself to that?

Because that’s how you win. Unless, of course, I don’t want a winning outcome, but to stay in my comfort zone – playing the same way that I usually do, but losing.

In business, disruption can lead to innovation. Harvard Business School professor Clayton Christensen describes disruption as something that “displaces and industry or market and produces something new, more worthwhile or efficient.” Forbes.com describes disruption as both, “destructive and creative.” Think Invisalign vs braces.

Sudden disruptions can happen to us at any time. For example, I have PCOS (Polycystic Ovarian Syndrome). When I was first diagnosed, I thought, “how am I going to live with this for the rest of my life?” It felt unfair, punitive, and overwhelming. Over time, I have learned how to manage it and see it as an impetus for positive, healthy living. It’s almost like I feel accountable to it. It’s the reason that I see exercise as a form of stress management, yoga as a healthy way to get a buzz, and am empowered by what my body can do as opposed to how my body looks.

I think the reason the concept of a ‘disruptor’ resonated with me because I realized that is what PCOS is.

It produced a new, efficient and worthwhile way of life.

It was both destructive and creative. Now, I can’t imagine living without it.

I see some women who could eat and drink whatever they wanted, struggling with weight gain after a pregnancy, or just over time as we have aged. I notice that many use food or alcohol as their only means of stress release (I do drink, by the way, just in case my friends are reading this and want to call me out). I hear women in stores and dressing rooms everywhere bemoaning not fitting into a pair of jeans or dreading bathing suit season. I’m not criticizing these women because I was one of these women. It’s just that I’m mostly over it now.

I’ve learned to love my lowest sustainable weight, not my skinny weight.

I’m proud that I can run a race or go on a long hike or bike ride on short notice because I stay active all of the time. I’m proud that my girls are more interested in their cross country running times than the size of their jeans, and that they think it’s worthwhile to empower other girls as opposed to competing for space, popularity or social media likes with them.

I’m proud because I never thought I would be a proponent of these behaviors before I was diagnosed with PCOS, and now I model them for my girls.

I’ve learned to respect and not fear the disruptor. Because of it, new inventions, systems and lives can be generated.

Subscribe to Fertile Health Happenings

* indicates required


Tell us a little about yourself


kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor

Being left out of the party

I was talking to my daughter the other day about why she shouldn’t post a picture on social media of a party that she attended because other kids who weren’t invited might feel sad and excluded seeing the post.
She persisted, but I was resolute. She finally agreed, but stomped away, mumbling how strict and uncool I was (both of which are true).
Why do I feel so strongly about this? Mostly due to working with infertility patients for the last 20 years who are often ‘left out of the party’.

Think about it.

Many women spend their 30’s either pregnant or breastfeeding. Most conversations revolve around topics related to challenges of these, i.e the number of dirty diapers in a day, breasts leaking at inappropriate times, what to do with young kids from 5- 7 pm when it was cold and dark outside and they were bored. Lunches and dinners consist of a discussion of the best products for babies or kids, I know this from personal experience. During this time period, I didn’t post much on social media, but if I did, it would be reflective of snapshots of this life: kids everyday, everywhere. Infertility patients are inundated with conversations and pictures of the family life that they hope to have at a time that they don’t have it yet. Sometimes I would complain about the struggles of having a young family and other times I would laugh about it, like when my daughter told everyone at my son’s baptism that she had lice. Either way, I developed a camaraderie with a group of my ‘mommy friends’ who were in the same life stage. We forged strong bonds as a result of learning how to be moms together. We were all attending the same party. How does a patient who is undergoing infertility treatments assimilate in this world?

In addition to social isolation, infertility patients also experience a lack of control. Consider when someone wants to lose weight. They go online, find exercises and diet tips, get a trainer, join a gym, maybe use some people’s own weight-loss journeys as motivation. Theoretically, if you create a calorie deficit, most likely you will lose some weight. Infertility patients can follow all of the rules, do everything that is asked of them, employ experts, and still may not conceive on a timeline acceptable to them. Consider the loss of control and frustration that ensues. It’s inescapable as reminders of other people’s fertility is present at all times of the day. Imagine being immersed in your own fertility journey and attending a baby shower during lunch at work. Considering going home and receiving an invitation to a baby shower in the mail or electronically. Reflect on relaxing at night while perusing social media and seeing picture after picture of women who seemingly conceive with ease.

My hope is that we are all aware that by living and celebrating our daily family life, we are tacitly, albeit unintentionally, creating an environment that isolates infertility patients and is a reminder of the lack of control they are having in their own lives. Of course, I’m not advocating that you don’t post pictures of your kids or your life, that would be unreasonable and hypocritical of me, as I, myself, do this often. But maybe we can use social media, in this case, as a reminder to be compassionate.

I was reading that a way to instill gratefulness into your life is to silently state something for which you are thankful every time you open a door. I’d love for you to consider that every time you post a picture, maybe you say a little prayer or put a kind thought out to the universe (if you’re not religious) for those who are struggling with infertility or pregnancy loss.

Subscribe to Fertile Health Happenings

* indicates required


Tell us a little about yourself


kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor

Behind the Scenes of a “Bad” Pregnancy Ultrasound

October is baby loss and miscarriage awareness month, so I thought I’d share a story with you about how I have been affected by this, both personally and professionally.

At 10 weeks, during my second pregnancy, I was told that my baby’s heartbeat stopped. Of course I was devastated, except that I did have a little nagging intuition that something ‘wasn’t quite right’ with this pregnancy which I had been hoping to disprove.

At the time, there was one sole physician at my practice, and I helped him with office procedures. He was away on a planned vacation, so it was up to me to cover the office. And, just to further add to my misery, my cat had escaped, my dad had received concerning test results and oh, it was my birthday.

I scheduled a D & C on a Friday because I couldn’t miss too many office days. I dropped my daughter off at my friend’s house then headed to the hospital with my husband, who didn’t know what to say, so he kept making jokes until I told him that I would punch him in the face if he didn’t stop. He stopped.

My sweet OB/GYNs (Drs Gennaro and Cahill) were there to do the procedure and, as always, were so kind and awesome. I tried to seem ok with it all, because oddly I didn’t want them to worry about me, and the procedure was uneventful. Once released from the hospital, I picked up my daughter (who was 14 months at the time) and we all headed home where my hubby asked if he could take a quick nap as this was “very stressful” for him (he actually is a great guy, but seriously?)

I returned to work that following Monday and my schedule was ironically crammed with pregnancy scans. I was wholeheartedly happy for all of the patients, as I knew most of them well and was part of their journeys so far, but there was an undercurrent of sadness for my own situation. I bottled up these feelings as they felt too self-indulgent and selfish.

Somehow, I got through that week, with my bottled-up feelings and conflicting emotions until that Friday. That day I did a pregnancy ultrasound on a patient and didn’t see a heartbeat.

We sat in silence for a bit while I searched, and she desperately wanted to hear what I desperately wanted to say. That all was ok. But I couldn’t. Because it wasn’t.

I felt my face get hot, my throat closed up and my eyes welled with tears at the same time that hers did. The words “I’m sorry” got caught in my throat, but they felt so inadequate that I didn’t say them. Her husband wasn’t there and she looked at me and asked if she lost the baby. I said that she had, and she just nodded. Then, eloquently, I said, “This sucks, this just *bleeping* sucks.” To my horror and amazement, she laughed and I cried at the same time. And not girl crying, by the way, but big, runny nose, unattractive, sobbing crying. Eventually, we both did.

They chose to have a D & C the following week, and I visited her in the recovery room and we chatted. She told me that I was so kind and caring, and I revealed what had just happened, as I felt like a fraud. I had used her experience to release my own feelings of loss, and for this I felt both empathetic and pathetic.

Ultimately, she conceived again, and delivered a healthy baby (as did I), and sent me a card thanking me for all that I did. How about that for grace. I’m not sure if I would have done the same if I was in her shoes.

I hear, from my patients and friends, that some clinicians are, well, not so great at delivering bad news and I can tell you, it’s not because they don’t care. It’s because they care too much. I am now actually grateful that I had this negative experience, as it has given me perspective that I tap into every single time I do a pregnancy scan. Now I don’t run from this discomfort, I lean into it. I allow myself to feel and absorb what this patient or couple is experiencing, and try to give them what they need, whether that is talking it through, not saying much, or sitting quietly while she (or they) cry and process the news.

I have also learned that people handle grief differently and no way is the wrong way. My husband tried to diffuse the situation with humor, then gave up and realized that caring for me and feeling what he felt was exhausting. I tried to make myself feel better by trying to make everyone around me feel better until it didn’t work anymore. My patient laughed until she cried.

If you have had this experience, you might have your own way of dealing with loss. And that’s ok. Just please realize that we, as your clinicians, may not say or do the ‘right’ thing, because we feel deeply for you and we handle this emotion in a variety of ways. Witnessing the naked emotion that is expressed when anticipation and cautious optimism becomes grief can be heartbreaking and can make us feel intrusive.

My fervent wish is that, as clinicians, we can learn to see our interaction at this time as a privilege and an opportunity to be the person that you need us to be.

Warmly,

Monica

kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor

Fertility Meds in a Nutshell, Part 1: The Oral Meds


Fertility meds don’t actually come in a nutshell. They come in the form of a pill or injections, depending on the type of medication. I’m going to address oral medications first, since they are usually the first step for those proceeding with fertility treatments. There are two different oral medications prescribed for fertility treatment in the United States: clomiphene citrate (Clomid) and letrozole (Femara).

Although they work in different ways, the end result of both is that the brain perceives low estrogen levels and makes more of a hormone called FSH. FSH can produce a follicle (egg) in those who don’t ovulate on their own, and many follicles in those who ovulate but need help achieving a pregnancy.

Both are good at their jobs, as most women who take them make follicles and ovulate, but they can come with a price. That is the way that the low estrogen levels can make you feel, especially on clomiphine. Estrogen is necessary to build a uterine lining, to make cervical mucus that is easy for sperm to penetrate, and contributes to a sense of well-being. Low estrogen, then, can be the cause of a thin uterine lining, unfavorable cervical mucus, hot flashes, mood swings, and an overall sense of not well-being. The good news is that <10% of women experiences these side effects, and these feelings do go away after the course of the medications. The bad news is that you can feel like a raging PMS monster. Don’t worry though – we have a Plan B and we can give you a medical clearance note if you want to punch someone.

That Plan B is letrozole. It is also good at its job, and has a short half-life. That means it leaves the body a short amount of time (about 48 hours) after taking it, so the body doesn’t have time to experience the anti-estrogen effects. So, why not just use letrozole first? Well, clomiphene is older and we know a lot about it, feel comfortable using it, it’s cheap and most insurances cover it. It’s also FDA-approved for making follicles (ovulation induction) and letrozole is not. Don’t let that scare you, though, we use a few medications in fertility treatments that are not FDA-approved for fertility treatments, but are safe and standards of care.

As mentioned before, the planned outcome for these is to make one to two follicles if you don’t normally ovulate and two to four follicles if you ovulate. The dose might be increased or decreased depending on your response, and many practices will ask you to have ‘relations’ (time intercourse appropriately) every day or every other day for a few days after stopping the medications.

If you are going to a fertility practice, they might administer a medication called a hCG or a trigger shot, that causes ovulation to occur in 36 hours, so we can precisely time intercourse or, a more proactive option, intrauterine insemination (IUI).

If you are on clomiphene and having any of the mood disturbances, make sure to tell your provider this. Continuing on clomiphene might not be the best choice for you as you are susceptible to its anti-estrogenic effects. If you are having an ultrasound after taking clomiphene and your uterine lining stays thin, you might be prescribed some estrogen during your cycle (after the clomiphene stops so as not to interfere with the brain’s perception of low estrogen), but you shouldn’t use clomiphene for subsequent cycles, as this effect will most likely continue.

Some women take progesterone (and sometimes estrogen) after ovulation until the pregnancy test. This is because your provider thinks (either due to blood levels or a shortened time from ovulation to menstrual cycle) that you have an insufficient luteal phase. The function of the corpus luteum, the cyst that is left after the egg ovulates out of the follicle, is to produce hormones, mostly progesterone, that make the uterine lining ready for the implantation of an embryo and, should pregnancy take place, support it until the placenta starts to work in a few weeks.
Low progesterone levels or a short (<14 days) period of time between ovulation and the next menstrual period, might be signs of an inadequate corpus luteum, so the concern is that an early implantation is not being supported. By giving you progesterone (and sometimes estrogen) we can, in fact, act as your body’s corpus luteum and support the uterine lining, and make it cozy for an embryo to implant there. Estrogen is given as an oral pill, and Progesterone is usually given as a vaginal suppository because oral progesterone doesn’t work so well for lining support.

Usually, a pregnancy test is done about two weeks after ovulation. If you are taking estrogen or progesterone, it can prevent a period from happening, so a blood test is necessary (since low levels of estrogen and progesterone generate a menstrual cycle, high levels can delay the start of one). If you are pregnant, expect to stay on the hormones for a few weeks. If not pregnant, you will stop them.

Most fertility treatments, if they are going to work, they will work in three to six months. If you don’t achieve a pregnancy after 3 months of therapy, it might be worthwhile to see your provider to talk about next steps (we have many options if oral therapy doesn’t work). If you are not ovulating or making follicles on oral therapy, you should talk to your provider sooner than three to six months, as you are not really getting a chance to achieve pregnancy those months and your time might be better spent trying a different medication regimen.

The chance of achieving a pregnancy per cycle is anywhere from 5-20% (depending on age, sperm count, and if you are doing an insemination or not). This is the actual chance that those who are not sub-fertile have each month of getting pregnant I know that you must know people who get pregnant just “looking at their husband” but for most people, the percent chance each month is lower than you would think.

Ultimately, these meds work very well for people and many get pregnant easily and quickly. For those of you who don’t, it’s important to know that there are other options, even though it’s disappointing. Also, now that you know what to expect, be sure to tell your healthcare provider if you experience uncomfortable side effects, and don’t think you are ovulating or think your period is coming quicker than it should.

Finally, no discussion on fertility treatment would be complete without mentioning the need to find and explore self-care methods. For some, it’s exercise. For others, reading a good book or journaling. Everyone, though, should feel free to limit contact with toxic people during this time. Ifyou can’t, like with a family member or weird co-worker, then just work on peacefully detaching when you are around them.

We, as women, are always taking care of those around us and it’s ok (and necessary) to give yourself permission to take care of you during your fertility journey. For other self-care ideas, see my blog on this and other subjects at www.fertilehealthexpert.com.[/vc_column_text][/vc_column][/vc_row]

monperatoto
monperatoto
slot gacor
monperatoto
monperatoto
monperatoto
slot gacor
monperatoto
monperatoto
monperatoto
monperatoto
togel online

situs gacor

live draw hk

link gacor

situs toto

slot gacor

toto togel

togel online

hongkong pools

slot kakek zeus

monperatoto

toto togel

slot resmi

live draw hk

situs togel

situs toto

kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor
situs slot

5 Email Subject Lines that only a Fertility Nurse (or Patient) Would Understand

As a fertility nurse, I know that we often receive emails from the front desk asking us to call a patient about a particular question or problem.


Although fertility treatments, and the challenges inherent in them, can be incredibly stressful (and this is not meant to minimize that) you might get a laugh from some of these. Whether you are a nurse or patient, I’m sure you can identify with many of these scenarios.


The following is a list of some recent (and real) email subject headings as well as a description of the situation and outcome.


  • 1) “Patient’s husband can’t leave a sample because there was a bat in the house and he’s very stressed out.”

We often joke about the male partner’s role in fertility treatments. The female has to do the bulk of the ‘work’: mix and administer injections, undergo blood draws and vaginal ultrasounds…etc.

All the man has to do is to provide the sperm sample. Well, we need to remember that the ‘act of providing’ the sample is somewhat dependent on the male being relaxed and in the mindset to ‘produce.’  Having any kind of added stress can be deleterious to the production process, to say the least. So in this particular situation, after chasing a bat around the house in the early morning hours, the last thing this poor guy wants to think about is producing into a cup. This can happen in even less eventful situations, like having an important work meeting or just feeling the stress of a positive ovulation predictor kit month after month.


If you think this might be an issue for your partner or your patient, have a back-up plan. Consider a frozen sample, or renting a local hotel room (seriously, sometimes the proximity to the office or escaping an office-like atmosphere can help). Although we often focus most of our care and attention on our female patients, this serves as a reminder not to forget about the men.

  • 2) “Please call patient, she has a meeting and can’t have her egg retrieval today.”

There are many variations of this: husband unable to bring in his sample due to traffic, unable to come in for a blood test or ultrasound due to bad weather … etc. Yes, there are many components of a fertility treatment cycle that are precisely timed, but there are some that can be modified.


Usually, the most flexibility occurs earlier on in a treatment cycle, so if you have to miss or reschedule an appointment, it can often be done then. If you have ‘blackout dates,’ or those days that you are unable to come into the office due to vacations or work conflicts, we can often plan around them, if we know in advance. There are some procedures, though, that are specifically timed and can’t be rescheduled, such as having an insemination or retrieval after your trigger shot. It’s still worth calling the office if you have a change in your schedule to see what can be rearranged and what can’t, but just know that some timing is beyond our control and rescheduling might be detrimental to your cycle. Regarding the semen sample timing, most centers are comfortable with the sample arriving within 45 -60 minutes of production (check with yours to see their policy). The sample should be kept close to body temperature, not frozen, for example, we had one male partner put his in a cooler with frozen veggies as he thought he would run errands on his way home from the grocery store.


  • 3) “Patient sneezed and her embryo fell out. She saved it, though, and can bring it in.”

So…this one, or some version of this, has come up almost every year since I’ve working in REI. Even though a blastocyst (an embryo at its implantation stage) is only the size of a period on a keyboard, infertility patients will obviously do anything to protect it and facilitate implantation.


We can only be so proactive to help implantation take place. Even when we do IVF, where we transfer the embryo directly in the uterus, it still floats around and finds a comfortable spot on its own, which can take a day or so. No amount of pressure (such as sneezing and going to the bathroom) will expel the embryo. Likely, what is being seen or felt is residue from vaginal medications, mucus or (yup) urine. So don’t worry if you sneeze or cough or yell. Your blastocyst is safely ensconced and is looking for (or found) its cozy spot.


  • 4) “Patient sent a picture of her butt and wants to know if she gave injection in the correct spot.”

Well, I have seen many butts, stomachs, and thighs over the years, and even seen some remotely (and abruptly) over FaceTime or Skype. Patients are taught how important it is to give the proper amount of medications, in the proper spot, and avoid big veins and the sciatic nerve. It’s no wonder they are so careful about where to give the injection. Even though we are happy to draw circles on their butts, when it is time to actually give the injection, it is still scary and nerve-wracking to give yourself or your partner an injection.


One of my patients asked her grandmother to help, because she is diabetic and used to giving injections. However, she didn’t take into account her grandmother’s poor eyesight issue, which generated an interesting injection site and caused some pain for the next few days. Also, sometimes, no matter how careful someone can be, there will be a little bleeding at the injection site, even moderate bleeding, because there are superficial blood vessels that can’t be avoided. Hitting these is ok, it just might cause a little bruise. We know that you’re nervous, so we are happy to draw circles, help with injections or look at your butt whenever necessary.


  • 5) “Patient’s dog ate her estrogen and she is wondering what to do.”

Fertility patients are very protective of their medications and with good reason. They are expensive, not easily obtained, very time-consuming and dose-specific. It can be overwhelming to receive the big box that is shipped and wonder, “what goes in the fridge?” or, “what needle do I use with what medication?” …etc.


I usually suggest separating and batching the medications and syringes, that is, putting stuff next to each other (or rubber banding it) that goes together. So, progesterone with progesterone needles, leuprolide with leuprolide needles…etc. As for the pills, many of them are not used until later, so they can be put away until you’re told to use them, in an effort to avoid any confusion and stay organized. It is helpful to keep the medications in a safe, climate-controlled area (unless they need to be refrigerated) away from kids, pets and nosy mother-in-laws who might snoop. Maybe in the master bathroom or in your bedroom, but out of reach. We have had cats knocking over and playing with medication vials, birds flying off with syringes, and dogs eating pills. By the way, the dog was ok, just a little breast tenderness.


Many of my colleagues and I really enjoy our roles as fertility nurses. We love taking care of our patients and helping them through the process, and absolutely understand that questions arise along the way. Hope that this answers a few of them and in the future, we will pick on the men a little more.

Subscribe to Fertile Health Happenings

* indicates required


Tell us a little about yourself


monperatoto
monperatoto
slot gacor
monperatoto
monperatoto
monperatoto
slot gacor
monperatoto
monperatoto
monperatoto
monperatoto
togel online

situs gacor

live draw hk

link gacor

situs toto

slot gacor

toto togel

togel online

hongkong pools

slot kakek zeus

monperatoto

toto togel

slot resmi

live draw hk

situs togel

situs toto

kampungbet

situs bola

toto togel

slot gacor hari ini

link gacor

toto slot

slot gacor

slot gacor

slot gacor

bandunghoki

situs toto

toto slot

situs toto

link gacor

slot gacor

toto togel

slot gacor
situs slot